
Bloating
Struggling with bloating? Here’s what you need to know to find relief.
ALL TEST ARE ACCREDITED & REGULATED BY


What is bloating?
When you’re bloated, your stomach or abdomen can feel full and uncomfortable, or even painful.
This bloating happens when your gastrointestinal tract contains too much gas or air. Bloating can be mild, or more severe, and may present as:
– A visibly distended or swollen abdomen
– Feeling very full and uncomfortable
– Feeling of tightness in the abdomen
– Excess gas – belching and/or flatulence
– Rumbling or gurgling
There are several causes of bloating, so it’s important to diagnose the cause of your bloating and find out why it’s happening to you.

Why does bloating happen?
Prolonged periods of bloating could indicate an underlying health problem, if so you should see your GP.
Possible causes can include:
Irritable bowel syndrome (IBS diagnosis)
Ulcerative colitis, a form of inflammatory bowel disease (IBD), where the inner lining of the large bowel is inflamed and develops ulcers
Crohn’s disease, the other form of IBD, where some parts of your colon are inflamed
Too much bacteria in your small intestine (called small intestinal bacterial overgrowth, or SIBO)
Gastroesophageal reflux disease
Food intolerances, especially lactose or fructose intolerance
Producing too much gas (dysbiosis and fermentation)
Weight gain
Stress or anxiety
Delays in your food and drink moving on from your stomach (called gastroparesis)
Eating too quickly, so that you swallow too much air (called aerophagia)

Diagnosing bloating
Feeling bloated is no fun, but once you know what’s going on you can start to manage your symptoms and the underlying causes.
Testing options:
At the Functional Gut Clinic, we can run the following tests to diagnose the causes of bloating:
Gastric emptying test– which measures how quickly food leaves your stomach
Carbohydrate malabsorption breath test– which finds out if you have certain food intolerances (lactose or fructose)
Small intestinal bacterial overgrowth (SIBO) breath test– which finds out if you have an overgrowth of bacteria in your small intestine (called SIBO)
Oesophageal manometry– which measures the function of your oesophagus (food pipe)
24-hour pH impedance monitoring– which looks at whether you have any reflux
Colonic transit study-a non-invasive test which looks at how long it takes for faeces to pass through your bowl
Learn more about bloating
IBS-C Symptoms vs Chronic Constipation
IBS isn’t just one condition. It’s split into several subtypes, depending on the prevalence of specific symptoms. IBS-C refers to the constipation-predominant type. It’s characterised by hard stools, straining, infrequent bowel movements, and a feeling of incomplete emptying.
But how do you distinguish IBS-C from chronic constipation?
Recurring abdominal pain associated with changes in bowel habit is what points more strongly towards IBS-C rather than functional constipation.
If you already have IBS-C and your current treatment has not provided enough relief, you can learn more about our current IBS-C research study.
What Is IBS-C?
IBS-C refers to irritable bowel syndrome with constipation predominance. It means constipation is the predominant bowel symptom alongside recurrent abdominal pain.
The confusion often comes when symptoms fluctuate or someone with IBS-C occasionally experiences diarrhoea. Other changes in bowel habit can occur, but constipation is predominant.
If diarrhoea predominates, a person may have IBS-D. If both constipation and diarrhoea are prominent, they may have IBS-M (mixed).
IBS-C Symptoms vs Functional Constipation
IBS-C and functional constipation can be difficult to tell apart. The primary difference is the recurring abdominal pain.
Here’s a quick overview of the two conditions:
Symptom | IBS-C | Functional Constipation |
Hard or lumpy stools | Common | Common |
Straining | Common | Common |
Infrequent bowel movements | Common | Common |
Incomplete emptying | Common | Common |
Bloating | Very common | Can occur |
Recurring abdominal pain | Central feature | May occur, but does not define the condition |
Pain linked to bowel movements | Characteristic | Less characteristic |
The diagnostic criteria for functional constipation mainly focuses on difficult or infrequent stool passage and specifically require that IBS criteria are not met. This is important as the treatments for the two conditions can be slightly different.
How Do Doctors Tell IBS-C and Chronic Constipation Apart?
There is no single test that confirms IBS-C or functional constipation. Doctors assess the pattern of symptoms and may use tests to check for other causes.
A GP will look at:
whether abdominal pain is present
whether pain changes after opening the bowels
stool frequency and consistency
how long symptoms have persisted
bloating and incomplete emptying
whether anything suggests another condition
The main diagnostic criteria are known as Rome IV[GU1]. For IBS, recurrent abdominal pain must be associated with at least two of the following: bowel movements, a change in stool frequency, or a change in stool form. Functional constipation, by contrast, is defined mainly by symptoms such as hard stools, straining, incomplete evacuation, or fewer than three spontaneous bowel movements per week without meeting IBS criteria.
Why Does Getting the Right Diagnosis Matter?
You might wonder why it matters. The distinction can determine treatment and eligibility for clinical research. IBS-C involves pain and other gut symptoms that may need attention alongside the constipation.
For example, low-dose amitriptyline may be considered for persistent IBS pain, but it can worsen constipation, so a clinician needs to weigh its benefits and risks.
Could My Symptoms Be Something Other Than IBS-C?
Neither IBS-C nor functional constipation should be self-diagnosed. A clinician can assess your symptoms and consider whether another condition needs investigating.
The NHS currently advises seeing a GP if suspected IBS symptoms have persisted for more than four weeks. Because symptoms can overlap with other conditions, your doctor may recommend blood tests, including a test for coeliac disease. Other tests depend on your symptoms and any warning signs.
Follow the link to read more about constipation symptoms and their potential complications.
What If My IBS-C Treatment Is Not Working?
IBS can be a difficult condition to treat because there is no single treatment that works for everyone. Instead, medications aim to minimise individual symptoms. For example, if constipation is the main problem, laxatives may be prescribed to soften stools and make them easier to pass. lifestyle changes
If your IBS-C treatment isn’t working, it doesn’t necessarily mean the diagnosis is wrong. However, it may be worth speaking to your GP about whether other treatment options or further investigation are appropriate.
Research is also ongoing into new approaches to IBS-C. Adults whose current treatment has not provided enough relief may wish to learn more about the IBS-C research study currently being conducted and decide whether taking part is something they would like to explore.
Ultimately, the key difference between IBS-C and chronic constipation is the wider symptom pattern, particularly recurrent abdominal pain and discomfort linked to bowel habit. If you are unsure which condition best fits your symptoms, speak to your GP for advice and appropriate assessment.
Read the following article: Thinking About Joining an IBS Clinical Trial? What to Expect and Questions to Ask

Hear from people we’ve helped, just like you.
"Very professional while welcoming and friendly"
"The manner and demeanour of all staff from reception to people carrying out the test was very professional but welcoming and friendly. Atmosphere is very relaxed and all instructions clear and concise."
London Patient

"Highly recommend this"
"Thanks to Dr Hobson and everyone at the Functional Gut Clinic. The whole team is very kind and generous and they are doing things that are cutting edge and they actually get results."
Manchester Patient
"Highly recommend this"
"After stopping my lansoprazole, every time I had a warm drink, I could feel it burn all the way down to my stomach. Thank you to Sam for making me feel at ease." - Manchester Patient
"My experience could not be better"
"Pleasant and knowledgeable staff that made the experience more enjoyable than it should be!" - London Patient
"Very friendly and knowledgeable"
"An excellent service from beginning to end. I would recommend to anyone who was considering having testing done. Very friendly and knowledgeable!" - Manchester Patient
"Very kind and helpful"
"It was also great to have time to talk to the clinicians – very important when you have problems. Reception staff also very kind and helpful." - Manchester Patient
Are you experiencing any other symptoms
Symptoms are often closely connected. Find out more below.
Reflux
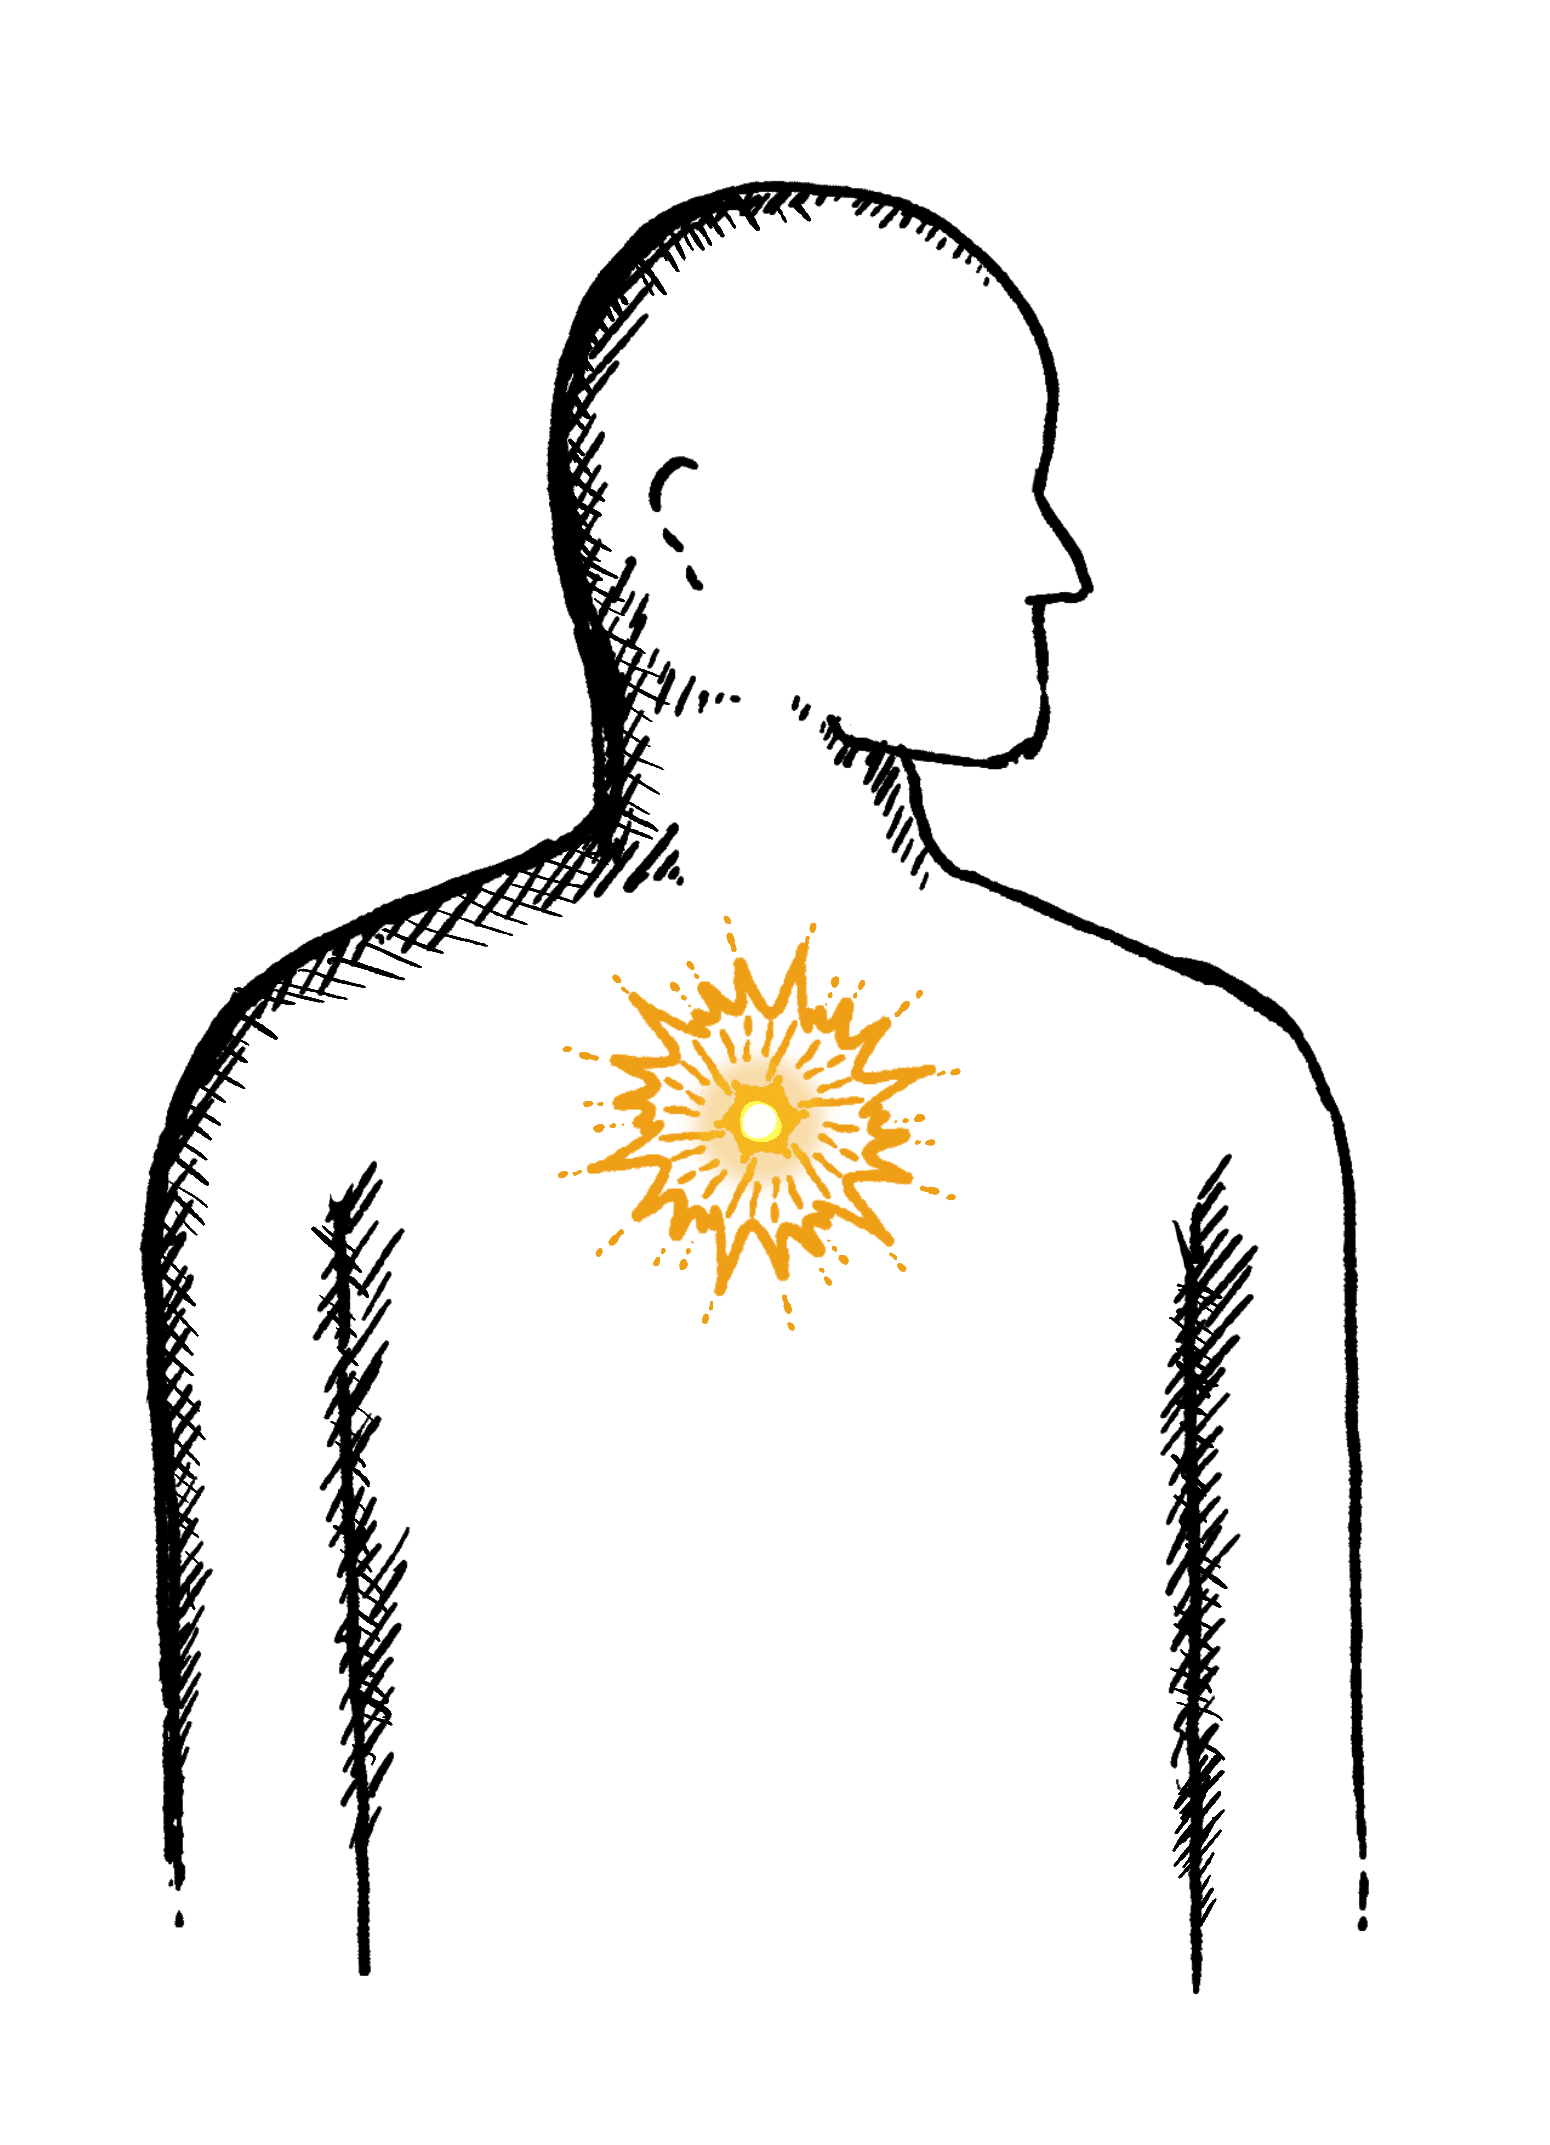
Burning mid-chest, worse when bending or lying down
Constipation
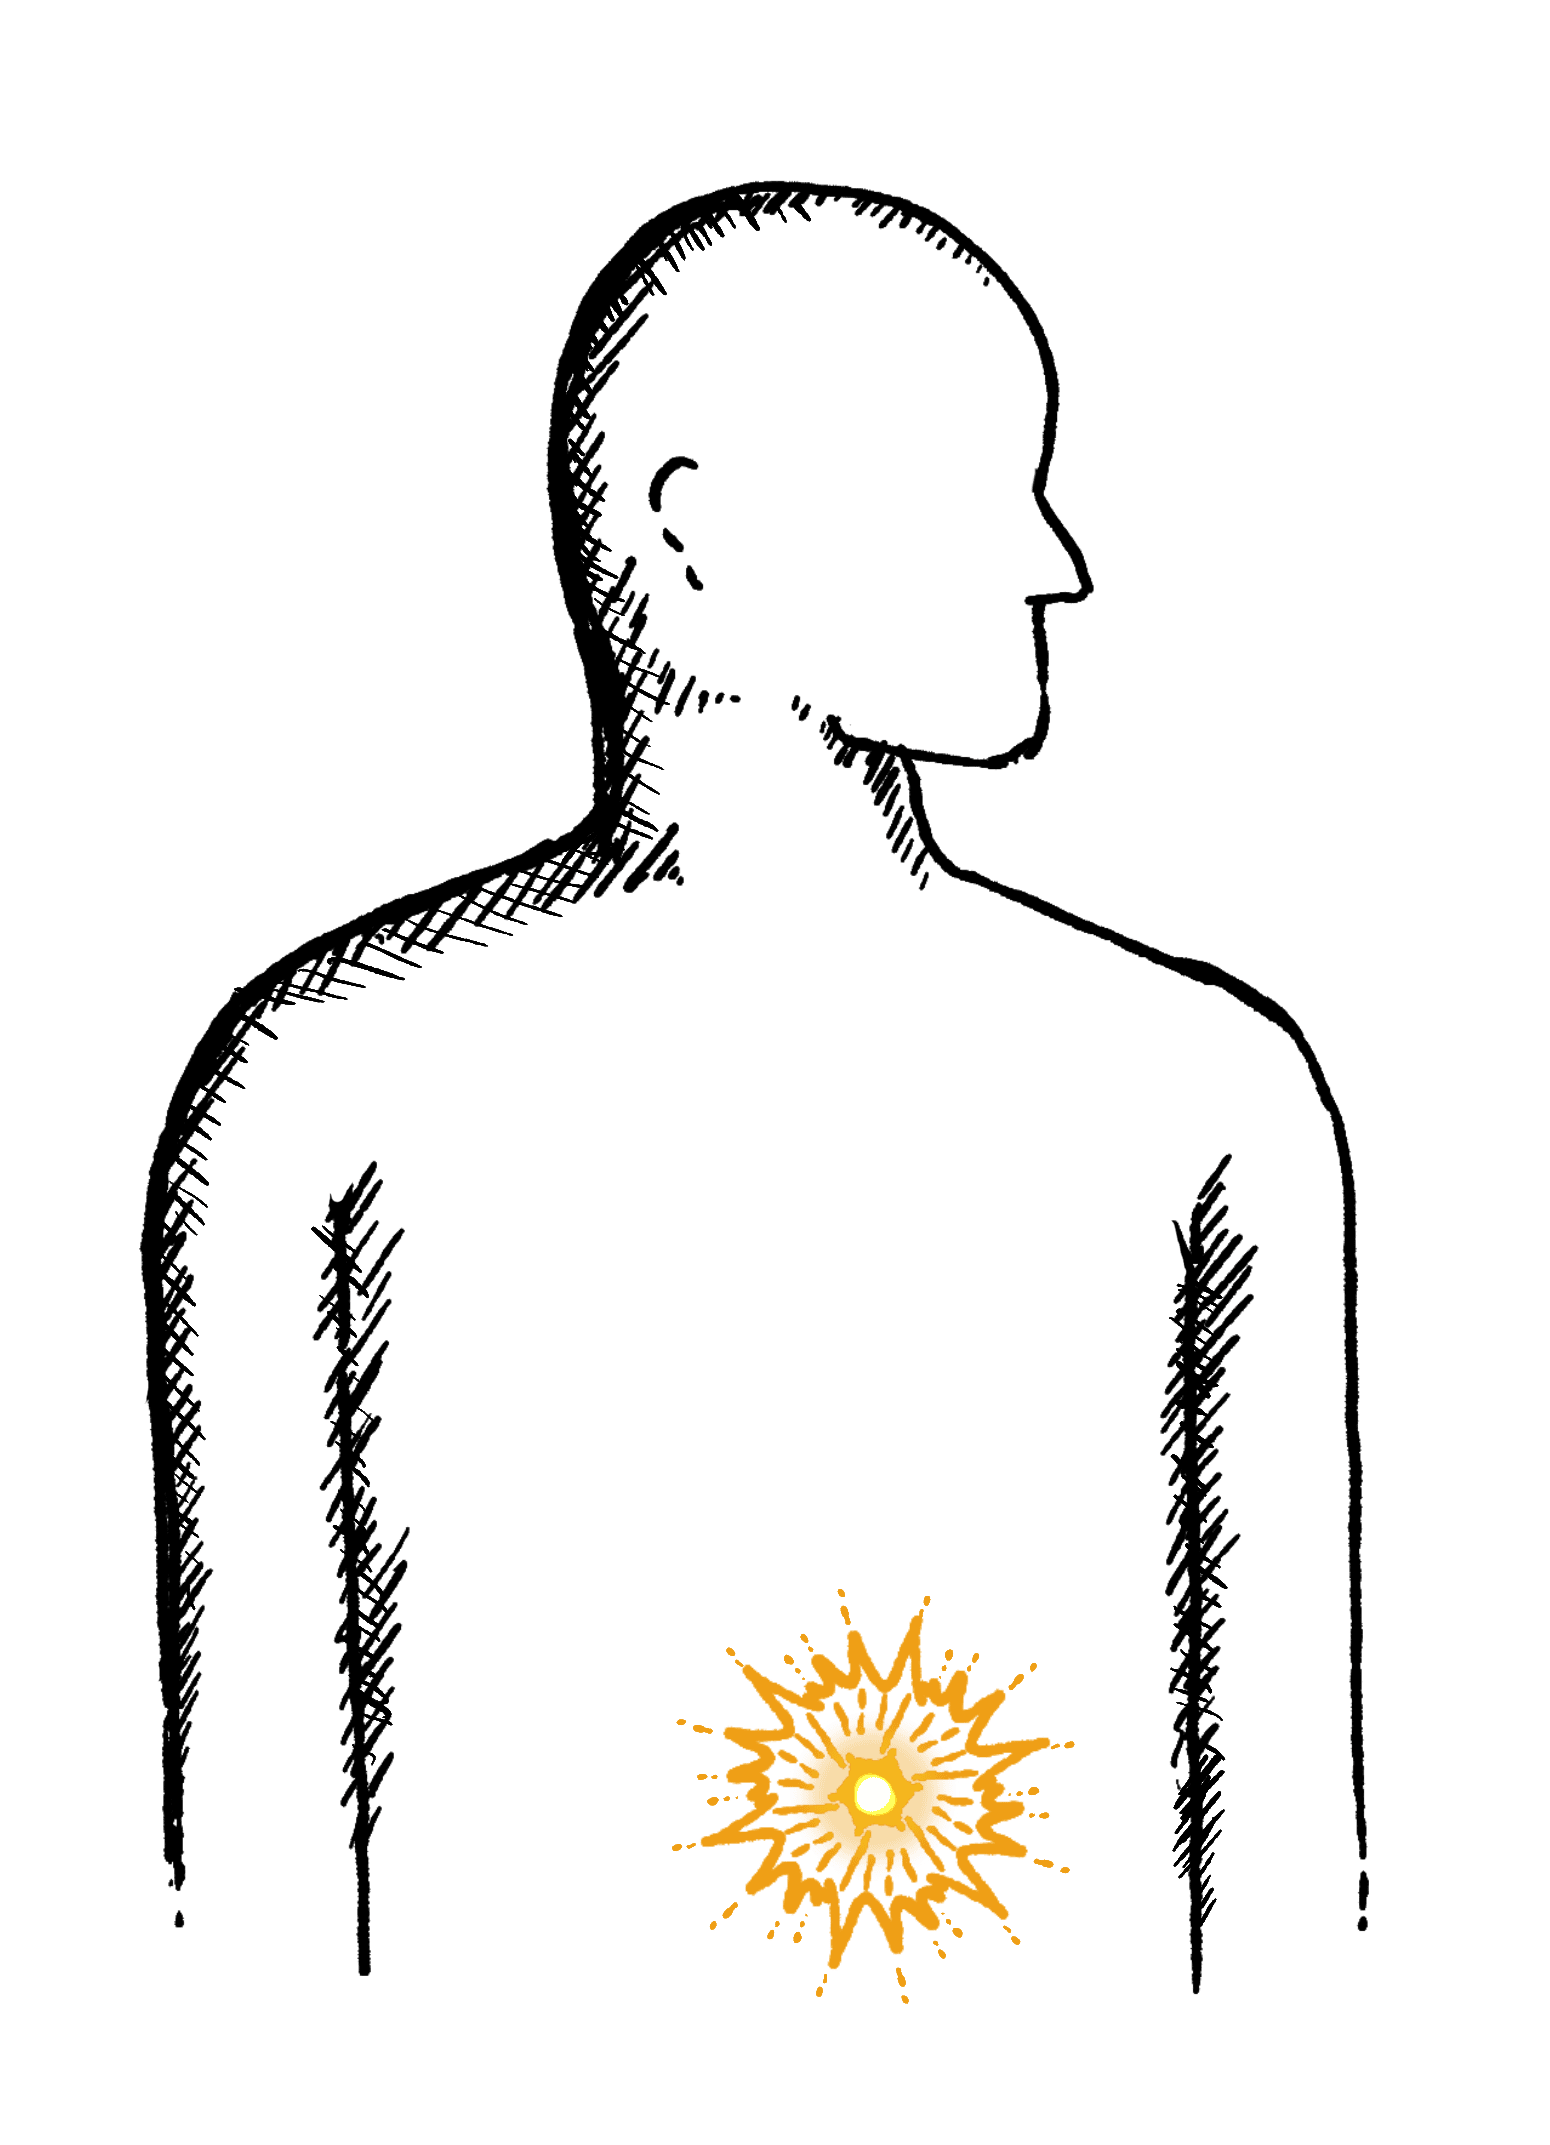
Difficulty going to the toilet, unusual stools, often with stomach ache or intestinal cramps, bloating, nausea or appetite loss
Heartburn
A burning pain in your chest, just behind your breastbone.
The pain is often worse after eating...
Regurgitation
Bringing food or drink back up, difficulty swallowing, feeling that food or drink is stuck in your throat, horrible taste in your mouth
Swallowing Issues
Dysphagia - difficulty swallowing, feeling that food or drink is stuck in your throat, horrible taste in your mouth
Diarrhoea
Loose or explosive stools, can’t get to a toilet in time
Abdominal Pain
Cramps; sharp or dull pain, Bloating, Excessive belching, Nausea or vomiting
Faecal Incontinence
Stools leak unexpectedly, Can’t get to a toilet in time
IBS
Abdominal pain or cramping, bloating, changes in bowel habits and urgency, gas
HEALTH ASSESSMENT
WHO WE ARE
HOW WE HELP YOU
LEARN
SUPPORT
FOLLOW US
© Copyright The Functional Gut Group 2026